

It’s not rare for someone to start a new medication for overactive bladder and suddenly find themselves unable to pee. No warning. No gradual change. Just a complete stop. This isn’t a coincidence-it’s a known, preventable side effect of anticholinergic drugs. And while these medications are often prescribed to reduce frequent urges to urinate, they can shut down the bladder’s ability to empty entirely. For men over 65 with even mild prostate enlargement, the risk jumps from less than 1% to over 4%. In some cases, it leads to emergency catheterization within days of starting the drug.
How Anticholinergics Disrupt Bladder Function
Your bladder doesn’t work like a simple water tank. It’s controlled by nerves and muscles that need to communicate perfectly. When you’re ready to urinate, your brain sends a signal through the parasympathetic nervous system. That signal releases acetylcholine, a chemical that binds to M3 receptors on the detrusor muscle-the main muscle in your bladder wall. When those receptors are activated, the muscle contracts, squeezing urine out.
Anticholinergic drugs block acetylcholine from binding to those M3 receptors. That’s the whole point: to reduce unwanted bladder contractions in people with overactive bladder. But if the detrusor can’t contract, the bladder can’t empty. Even if the urethra is open, the bladder just sits there, full and silent. That’s urinary retention.
Not all anticholinergics are the same. Oxybutynin, one of the oldest and most prescribed, blocks M1, M2, and M3 receptors equally. That means it hits not just the bladder, but also the brain (causing brain fog), the mouth (causing dryness), and the gut (causing constipation). It’s also the most likely to cause retention-studies show men with prostate issues have over three times the risk compared to placebo. Solifenacin and darifenacin are more selective for M3 receptors, so they’re slightly safer. But even then, the risk doesn’t disappear.
Who’s at the Highest Risk?
Men over 65 with benign prostatic hyperplasia (BPH) are the most vulnerable. Their prostate is already pressing on the urethra, making it harder for urine to flow. Add an anticholinergic on top, and the bladder loses its ability to push through that blockage. A 2019 University of Calgary review found that in this group, the risk of drug-induced retention rises to 4.3%. For women, the risk is lower-around 5%-but still real, especially if they’ve had pelvic surgery or nerve damage.
It’s not just age and prostate size. The more medications you take, the higher the risk. If you’re on an anticholinergic plus an opioid, an antihistamine, or a tricyclic antidepressant, your total anticholinergic burden adds up. The Anticholinergic Cognitive Burden (ACB) scale scores drugs from 1 to 3 based on how strongly they block acetylcholine. A score of 3 or higher is linked to a 68% increased chance of urinary retention in older adults.
People with dementia are especially at risk. The Beers Criteria, used by doctors across North America to avoid harmful drugs in seniors, lists anticholinergics as potentially inappropriate. A 2016 JAMA Internal Medicine study found anticholinergic use increased urinary retention risk by 49% in dementia patients-not because of the disease itself, but because of the drugs.
Real Stories, Real Consequences
On Drugs.com, a 68-year-old man named JohnM72 wrote: “After two weeks of oxybutynin 5mg, I couldn’t pee at all. They had to insert a catheter. My urologist said this happens in 1 out of 50 men my age with even a little prostate enlargement.” That’s not an outlier. A 2022 survey of 1,234 anticholinergic users found that 8.7% had to be catheterized because they couldn’t urinate. Two-thirds of those cases happened within the first 30 days.
Reddit’s r/urology community has over 120 posts since 2020 about people who suddenly couldn’t pee after starting tolterodine, oxybutynin, or solifenacin. One man, 71, ended up in the ER after taking a single dose. Another woman, 73, described feeling “like a water balloon about to burst” before being rushed to the hospital.
But not all stories are negative. A woman named CathyR on HealthUnlocked shared: “My urologist checks my post-void residual every month. I’ve been on solifenacin 5mg for 18 months without issues because we caught my residual creeping up to 150mL and dropped my dose right away.” That’s the key: monitoring.
What Doctors Should Do Before Prescribing
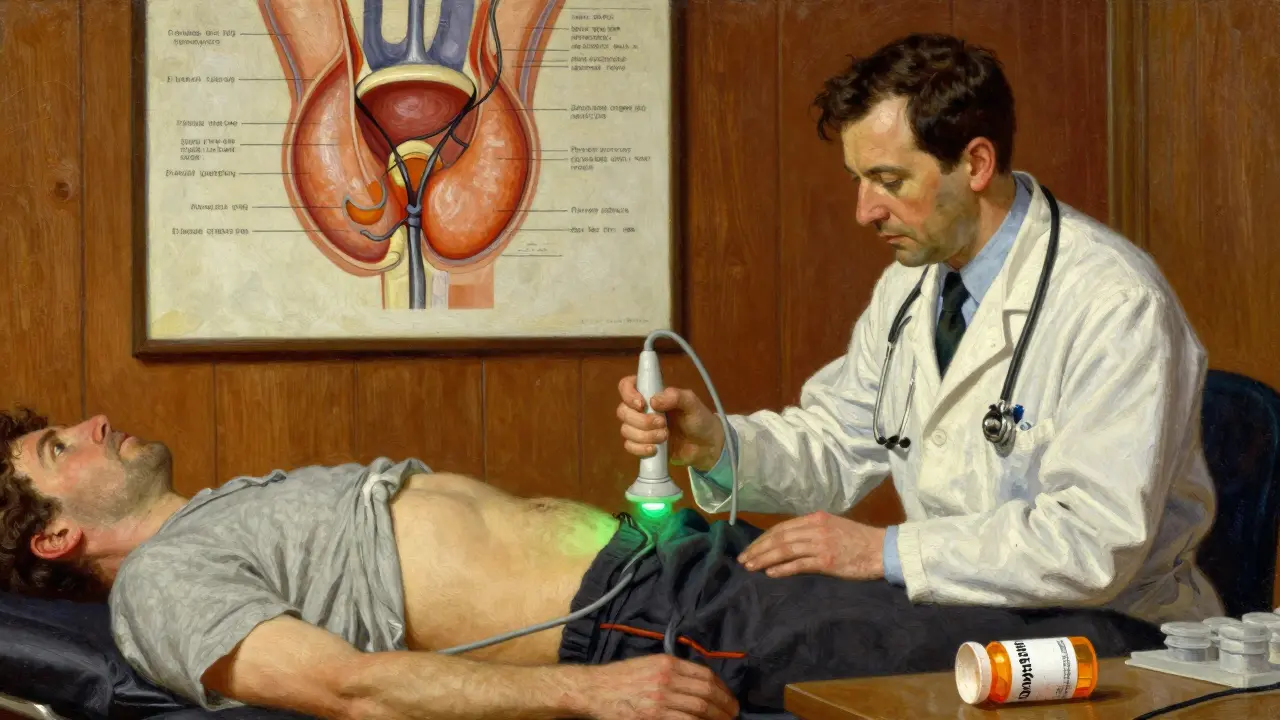
The American Urological Association (AUA) guidelines are clear: before starting any anticholinergic in a man, you must measure the post-void residual (PVR)-the amount of urine left in the bladder after peeing. This is done with a simple ultrasound device called a bladder scanner. It takes less than five minutes. No needles. No pain.
If the PVR is over 150mL, don’t start the drug. Period. If it’s between 100 and 150mL, proceed with extreme caution and check again in one week. If it climbs, stop the drug. Many doctors skip this step because they don’t have the equipment or training. But the International Continence Society requires 20 supervised scans before certifying a provider to use these devices.
For women, baseline PVR isn’t always mandatory-but it should be, especially if they’re over 60 or have had pelvic surgery. A 2020 Practice Management study found that urologists spend an average of 8.2 minutes per PVR check. That’s time well spent. A single missed scan can lead to an emergency room visit costing over $2,000.
Alternatives That Don’t Risk Retention
There are better options. Mirabegron, a beta-3 agonist, works differently. Instead of blocking signals to the bladder, it activates a different pathway that relaxes the detrusor muscle. In clinical trials, its retention rate was 0.3%-a tenth of anticholinergics’ 1.7%. It’s now the first-line choice for men with overactive bladder and prostate issues.
OnabotulinumtoxinA (Botox) injections into the bladder wall are another alternative. They paralyze the muscle temporarily, reducing urgency and frequency. Retention risk is only 0.5%, and if it happens, it’s usually temporary and treatable with intermittent catheterization.
For patients who want to avoid injections or pills, peripheral neuromodulation-like PTNS (percutaneous tibial nerve stimulation)-is a non-drug option. It uses mild electrical pulses to retrain bladder nerves. Success rates are similar to anticholinergics, with no risk of retention.
How to Reduce Risk If You Must Use Anticholinergics
If your doctor insists on trying an anticholinergic, there are ways to lower the danger:
- Start low, go slow. Begin with 25% of the standard dose. Wait two weeks. Only increase if needed.
- Use patches or gels. Oxybutynin skin patches have 42% lower retention risk than pills because they deliver the drug more steadily.
- Add an alpha-blocker. If you have BPH, taking tamsulosin or alfuzosin with an anticholinergic reduces retention risk by 37% by relaxing the prostate and urethra.
- Monitor closely. Get a PVR check after one week, then monthly. If your residual rises above 150mL, stop the drug.
- Know the warning signs. Straining to start urinating, weak stream, feeling like you haven’t finished, or needing to push-these are red flags. If you can’t pee for 12 hours, go to the ER.
Home bladder scanners are now available for purchase. A 2021 pilot study found that using one at home increased monitoring adherence by 92% and cut retention episodes by 61%.
The Bigger Picture: Why This Matters
Over 15 million Americans are prescribed anticholinergics for overactive bladder each year. That’s $2.3 billion in sales. But the cost to the system is higher: $417 million annually in ER visits, catheterizations, and hospital stays. The FDA now requires black box warnings on all anticholinergic labels. The European Medicines Agency banned them outright in patients with a history of retention.
Market trends reflect the shift. In 2015, anticholinergics made up 58% of overactive bladder prescriptions. By 2022, that dropped to 36%. Mirabegron now holds 31% of the market. Doctors are learning: the risk isn’t worth it for many patients.
Emerging tools are making prevention easier. The Anticholinergic Risk Calculator (ARC), launched in 2023, uses age, prostate size, baseline PVR, and other meds to predict your personal retention risk with 89% accuracy. Genetic testing for CHRM3 receptor variants may soon identify those genetically prone to retention-people who should never take these drugs at all.
By 2025, the AUA is expected to recommend avoiding all anticholinergics in men with prostate volumes over 30mL. That’s a major shift. These drugs were once first-line. Now, they’re third-line-for men.
For women, they’re still often used. But even there, the tide is turning. The safest path isn’t always the most familiar one. It’s the one that keeps you peeing-not stuck.
Can anticholinergic medications cause complete urinary retention?
Yes. Anticholinergic drugs block the nerve signals that tell the bladder muscle to contract. Without that contraction, urine can’t be pushed out, even if the urethra is open. This can lead to complete urinary retention-where you cannot urinate at all. Acute cases often require emergency catheterization. Studies show up to 8.7% of users experience retention severe enough to need this intervention.
Which anticholinergic drugs have the highest risk of causing urinary retention?
Oxybutynin carries the highest risk due to its non-selective action on multiple muscarinic receptors, including M3, which controls bladder contraction. Studies show it has a 2.1-fold higher risk of retention compared to tolterodine in men with prostate enlargement. Solifenacin and trospium chloride are moderately risky, while darifenacin and mirabegron (a non-anticholinergic) are safer alternatives.
Why are men over 65 more at risk than women?
Men over 65 are more at risk because many have benign prostatic hyperplasia (BPH), where the prostate enlarges and compresses the urethra. This already makes urination harder. Anticholinergics reduce the bladder’s ability to contract forcefully, so the weakened stream can’t overcome the blockage. Women don’t have this anatomical factor, so their risk is lower-though still present, especially with prior pelvic surgery or nerve damage.
What is a post-void residual (PVR) test, and why is it important?
A post-void residual (PVR) test measures how much urine remains in the bladder after you urinate. It’s done with a handheld ultrasound device called a bladder scanner. A PVR over 150mL indicates poor bladder emptying and signals high risk for retention. Guidelines require this test before starting anticholinergics in men. Without it, doctors can’t tell if the drug is causing harm until it’s too late.
Are there safer alternatives to anticholinergics for overactive bladder?
Yes. Mirabegron, a beta-3 agonist, relaxes the bladder muscle without blocking acetylcholine and has a retention risk of only 0.3%. OnabotulinumtoxinA (Botox) injections into the bladder wall are another option with 0.5% retention risk. For non-drug approaches, peripheral neuromodulation (like PTNS) retrain bladder nerves with no systemic side effects. These are now preferred over anticholinergics, especially for men.
What should I do if I can’t urinate after starting a new medication?
If you haven’t been able to urinate for 12 hours or more, go to the emergency room immediately. Do not wait. Acute urinary retention can cause bladder damage, kidney injury, or infection. Tell the staff you’re on an anticholinergic medication. They’ll likely insert a catheter to drain your bladder and may discontinue the drug. Bring your medication list with you.
Can I reduce my risk by lowering the dose?
Yes. Starting at a lower dose-like 25% of the standard amount-and increasing slowly can reduce the risk. Many patients respond well to half-doses. Also, switching from oral pills to a skin patch (like oxybutynin patch) lowers retention risk by 42% because the drug enters the bloodstream more slowly. Always discuss dose changes with your doctor before making them.
Is it safe to take anticholinergics with other medications?
It’s risky. Many common drugs-like antihistamines (Benadryl), tricyclic antidepressants (amitriptyline), and opioids (oxycodone)-also have anticholinergic effects. When combined, they add up. The Anticholinergic Cognitive Burden (ACB) scale scores drugs from 1 to 3. A total score of 3 or higher significantly increases retention risk. Always review all your meds with your doctor or pharmacist.
Corey Chrisinger
January 15, 2026 AT 22:58Bianca Leonhardt
January 16, 2026 AT 11:03Travis Craw
January 16, 2026 AT 15:18brooke wright
January 17, 2026 AT 18:16vivek kumar
January 18, 2026 AT 19:10Nick Cole
January 20, 2026 AT 17:31Riya Katyal
January 20, 2026 AT 20:29Henry Ip
January 21, 2026 AT 20:04waneta rozwan
January 22, 2026 AT 00:20